Uterine Sarcoma Surgery in West Delhi | Dr. Sarika Gupta
Hearing the words “uterine sarcoma” can be frightening. It is a rare cancer, and unlike common fibroids, it needs a very different approach to diagnosis and treatment.
The first question many women have is simple: “What happens next?”
In most cases, surgery is an important part of treatment. But the operation is not the same for everyone. The type of sarcoma, its size, where it is located and whether it has spread all affect the surgical plan.
Dr. Sarika Gupta is Director and Unit Head of Gynae Oncology at Action Cancer Hospital, Paschim Vihar. She treats gynaecological cancers and performs open, laparoscopic and robotic cancer surgeries when they are appropriate for the patient.
This guide explains the basics of uterine sarcoma, the role of surgery and what patients can expect before and after an operation.
Why experience matters in uterine sarcoma surgery
Uterine sarcoma is a group of cancers rather than one single disease. Leiomyosarcoma and endometrial stromal sarcoma are two examples. Their behaviour and treatment can be different.
That is why the operation should be planned around the pathology and imaging, not simply around the size of the uterus or the presence of a “fibroid.”
Dr. Sarika Gupta has more than 21 years of surgical experience in gynaecologic oncology. She has worked at Rajiv Gandhi Cancer Institute & Research Centre and Indraprastha Apollo Hospitals in New Delhi.
She also completed clinical fellowship training in Gynae Oncology and Robotics at the Florida Cancer Institute in the USA and underwent surgical observation at Memorial Sloan Kettering Cancer Center.
At Action Cancer Hospital, her work includes complex gynaecological cancer surgery, including minimally invasive and robotic procedures for patients who are suitable candidates.
What are the symptoms of uterine sarcoma?
The symptoms can be confusing because they may look similar to problems caused by fibroids or other gynaecological conditions.
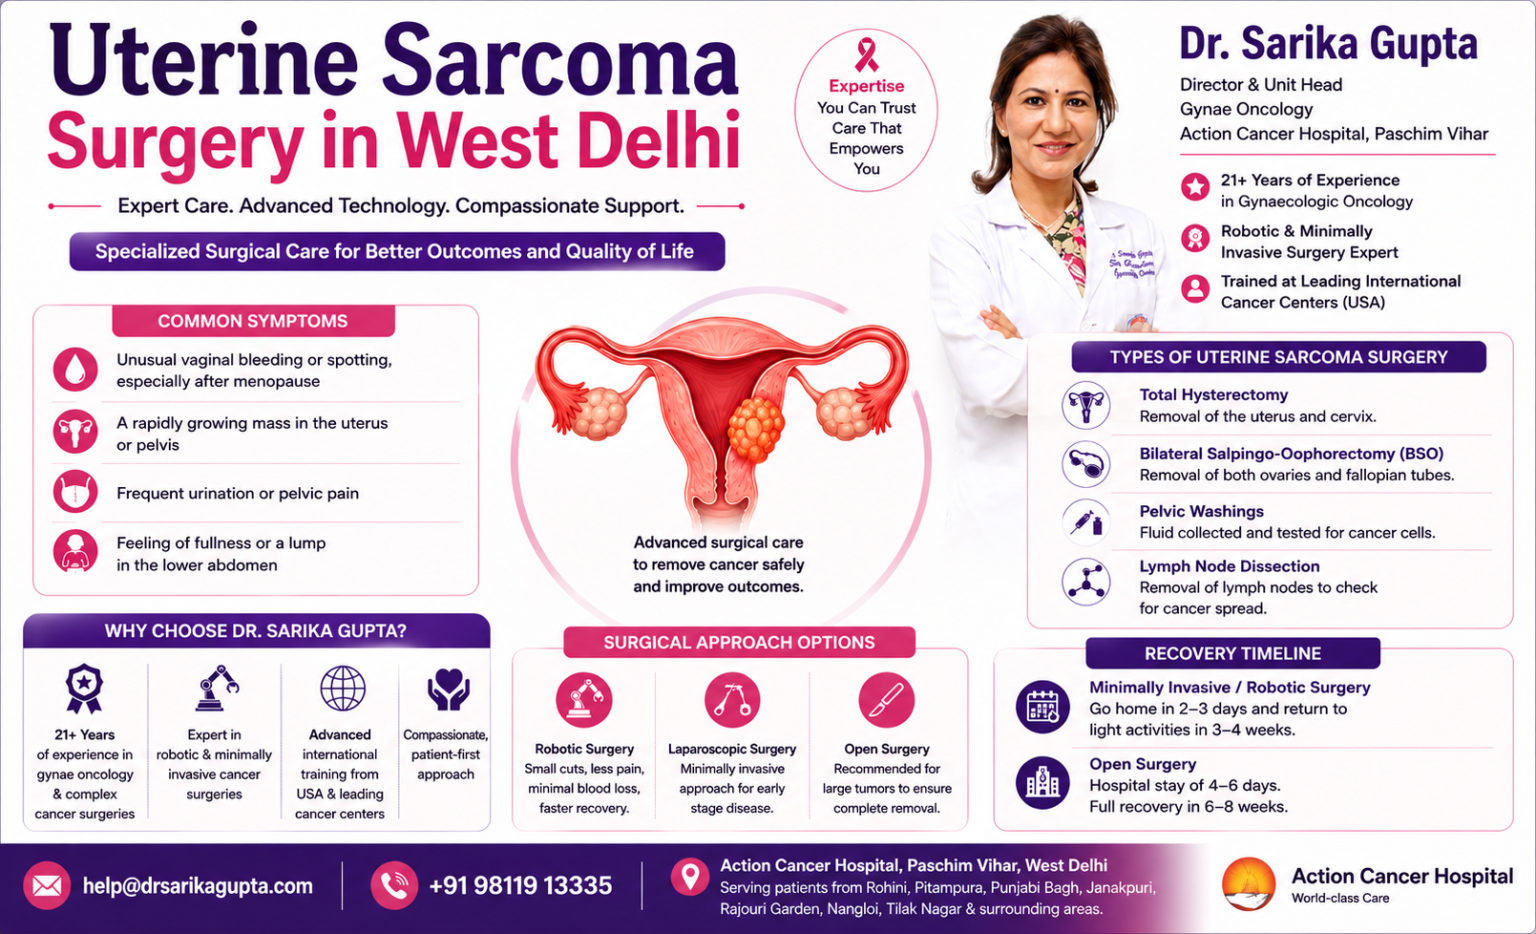
Possible symptoms include:
- Bleeding or spotting that is unusual for you, especially bleeding after menopause
- A uterus or pelvic mass that appears to be growing quickly
- Pelvic pain, pressure or discomfort
- Frequent urination because of pressure on the bladder
- A feeling of heaviness or fullness in the lower abdomen
Having one of these symptoms does not mean you have sarcoma. Most uterine masses are not sarcomas. Still, unusual bleeding or a rapidly changing uterine mass should be investigated.
This is particularly relevant after menopause, when new bleeding should not simply be assumed to be a hormonal problem or fibroid related.
When is surgery needed?
Surgery is commonly used to treat uterine sarcoma and can also provide important information about the extent of the disease.
Depending on the situation, surgery may involve removal of the uterus, cervix, fallopian tubes and ovaries. In selected cases, lymph nodes or other areas may also need to be examined or removed.
For some women with more advanced disease, the surgical team may consider cytoreductive surgery, where the aim is to remove as much visible tumour as safely possible.
The decision is not based on one scan or one symptom. Pathology, imaging and the patient’s overall health all matter.
What does the surgery involve?
There is no universal “uterine sarcoma operation.” The procedure is planned according to the individual case.
Hysterectomy
A total hysterectomy removes the uterus and cervix. This is commonly part of surgery for uterine sarcoma.
Removal of the ovaries and fallopian tubes
The surgeon may recommend removing both ovaries and fallopian tubes. This decision depends on factors such as the type of sarcoma, the patient’s age and the stage of the disease.
For a younger woman, the question of ovarian removal can be especially important because it may cause immediate menopause. It should be discussed before surgery.
Lymph node assessment
Lymph nodes may be removed in selected cases to determine whether the cancer has spread. This is not automatically required for every type of uterine sarcoma.
Pelvic washings
In some operations, fluid from the abdominal or pelvic cavity is collected and sent to the laboratory. The sample is examined for cancer cells.
Open, laparoscopic or robotic surgery?
This is one of the questions patients often ask after hearing that minimally invasive surgery is available.
The smallest incision is not automatically the best choice in cancer surgery. The first priority is removing the cancer safely.
Open surgery
Open surgery, or laparotomy, uses a larger abdominal incision. It may be needed when the tumour or uterus is large or when the surgeon needs wider access to the abdomen and pelvis.
In suspected sarcoma, the surgeon also wants to avoid breaking the tumour during removal.
Laparoscopic surgery
Laparoscopic surgery uses small abdominal incisions and a camera. For carefully selected patients, it can mean less postoperative discomfort and a quicker recovery.
It is not suitable for every sarcoma. The decision depends on the tumour and whether it can be removed safely without fragmentation.
Robotic surgery
Robotic surgery is also minimally invasive. The surgeon controls the robotic instruments while viewing the surgical area through a high definition 3D system.
For the right patient, it can mean smaller incisions, less blood loss and a shorter recovery than open surgery. But it is not automatically the right approach simply because it is newer technology.
For uterine sarcoma, the cancer and the surgical plan come first.
Patients from areas such as Rohini, Pitampura, Peeragarhi, Punjabi Bagh, Janakpuri and Rajouri Garden may seek consultation at Action Cancer Hospital, Paschim Vihar.
What is recovery like?
There is no single recovery timeline.
Someone who has a robotic or laparoscopic procedure may return home within a few days and gradually return to normal activities over the next few weeks. Open surgery usually takes longer, with several days in hospital and a recovery period that can extend to six weeks or more.
Heavy lifting and strenuous exercise are generally restricted during the early recovery period. Sexual activity also needs to wait until the surgical area has healed sufficiently.
The exact advice should come from your surgeon because the recovery period depends on what was actually done during the operation.
What are the possible complications?
Like any major operation, uterine sarcoma surgery has risks.
These may include bleeding, infection, blood clots, urinary problems or injury to nearby structures such as the bladder, ureters or bowel.
If lymph nodes are removed, there is also a risk of lymphoedema, which can cause swelling in the legs.
For women who have their ovaries removed before natural menopause, surgery can also lead to sudden menopausal symptoms.
Your surgeon should explain the risks before you consent to the procedure and tell you which ones are most relevant to your particular operation.
What happens after surgery?
Surgery is not necessarily the end of treatment.
The pathology report helps determine the exact type of sarcoma and provides information about its behaviour and stage. Based on those findings, the oncology team may recommend observation, chemotherapy, radiation or another treatment.
Follow-up is also important because some uterine sarcomas can return.
The schedule varies. Follow-up appointments may include physical and pelvic examinations, with scans such as CT, MRI or PET-CT when they are considered necessary.
Is a second opinion worth considering?
For a rare cancer, getting another opinion can be useful. It does not mean you distrust your first doctor. Sometimes you simply want to understand the diagnosis and options before making a decision about major surgery.
A second opinion may be particularly useful if:
- You have been told that a uterine mass is a rapidly growing fibroid.
- Sarcoma has been diagnosed and you want another opinion about the surgical plan.
- You have been offered robotic or laparoscopic surgery and want to know whether it is safe in your case.
- You have been advised to undergo extensive surgery and want to discuss alternatives.
Women from West Delhi areas such as Nangloi and Tilak Nagar can consult a gynaecologic oncologist at Action Cancer Hospital, Paschim Vihar, for assessment of complex uterine masses and confirmed gynaecological cancers.
Frequently asked questions
Is uterine sarcoma the same as endometrial cancer?
No. Endometrial cancer starts in the inner lining of the uterus. Uterine sarcoma develops from the muscle or supporting tissues of the uterus. They are different cancers.
Can sarcoma look like a fibroid?
Yes. This is one reason these cases can be difficult to diagnose. A sarcoma may look like a fibroid on imaging.
Rapid growth can be a warning sign, particularly after menopause, but growth alone does not prove that a mass is cancerous.
Why should the tumour not be broken during surgery?
If a malignant tumour is fragmented, cancer cells can potentially spread into the abdominal or pelvic cavity. For suspected uterine sarcoma, surgeons therefore plan the operation carefully to remove the tumour without unnecessary fragmentation.
Will chemotherapy be needed after surgery?
It depends.
The answer is based on the type of sarcoma, stage, pathology and other risk factors. Some patients need additional treatment after surgery, while others may be followed without chemotherapy.
How long does robotic surgery take?
There is no fixed time. The duration depends on the size of the uterus or tumour and whether procedures such as lymph node assessment are also required.
Does insurance cover robotic surgery?
Insurance coverage varies between policies and insurers. Patients should check their policy and confirm pre-authorisation requirements with the hospital before surgery.
The most important thing to remember
A uterine sarcoma diagnosis needs a treatment plan built around the individual patient. The type of tumour, stage and pathology matter more than simply choosing between open, laparoscopic or robotic surgery.
If you have been diagnosed with uterine sarcoma, or have a uterine mass that needs further evaluation, speaking with a gynaecologic oncologist can help you understand what the reports mean and what options are available.
Dr. Sarika Gupta, Director and Unit Head of Gynae Oncology at Action Cancer Hospital, Paschim Vihar, provides consultation and surgical treatment for gynaecological cancers, including complex uterine cancers.

Dr. Sarika Gupta
Director and Unit Head of Gynae Surgical Oncology at Action Cancer Hospital.